
Cynthia Chude follows the paper trail from a diabetes diagnosis to a lost limb — discovering that outcomes often turn on billing codes, referral rules, and a patient’s zip code.

Cynthia Chude spends her days with Medicare claims data, following patients down a path nobody should have to walk. An MD/PhD candidate — a doctoral candidate at the Wharton School and a medical student at Meharry Medical College — and a 2025 Escarce-Kington Scholar, she studies lower-limb amputation: who gets one, who doesn't, and why.
Her dissertation asks one question: how does the health-care system decide who loses a limb, what happens to them after, and how can care be redesigned so fewer people reach that outcome at all?
The answer, she has found, is not always medicine.
At amputee support groups, Chude heard the same story again and again. "My mom had diabetes, my aunt had diabetes, and they all got an amputation," patients told her. Many had come to believe that losing a leg is simply what diabetes does. "They don't understand that that is an adverse outcome," she said. "That should not be part of our normal course of care."
The comparison Chude reaches for is the heart. Patients with clogged coronary arteries expect stents and bypasses; decades of public-health effort taught them to check their blood pressure and know their options. "No one in their normal thinking mindset" expects a surgeon to remove the heart itself, she said. Yet the same disease in the legs — peripheral arterial disease, the same cholesterol clogging the same kind of vessel — too often ends at the saw.
If we can unclog those arteries in your heart, we have tools to unclog the ones in your legs.
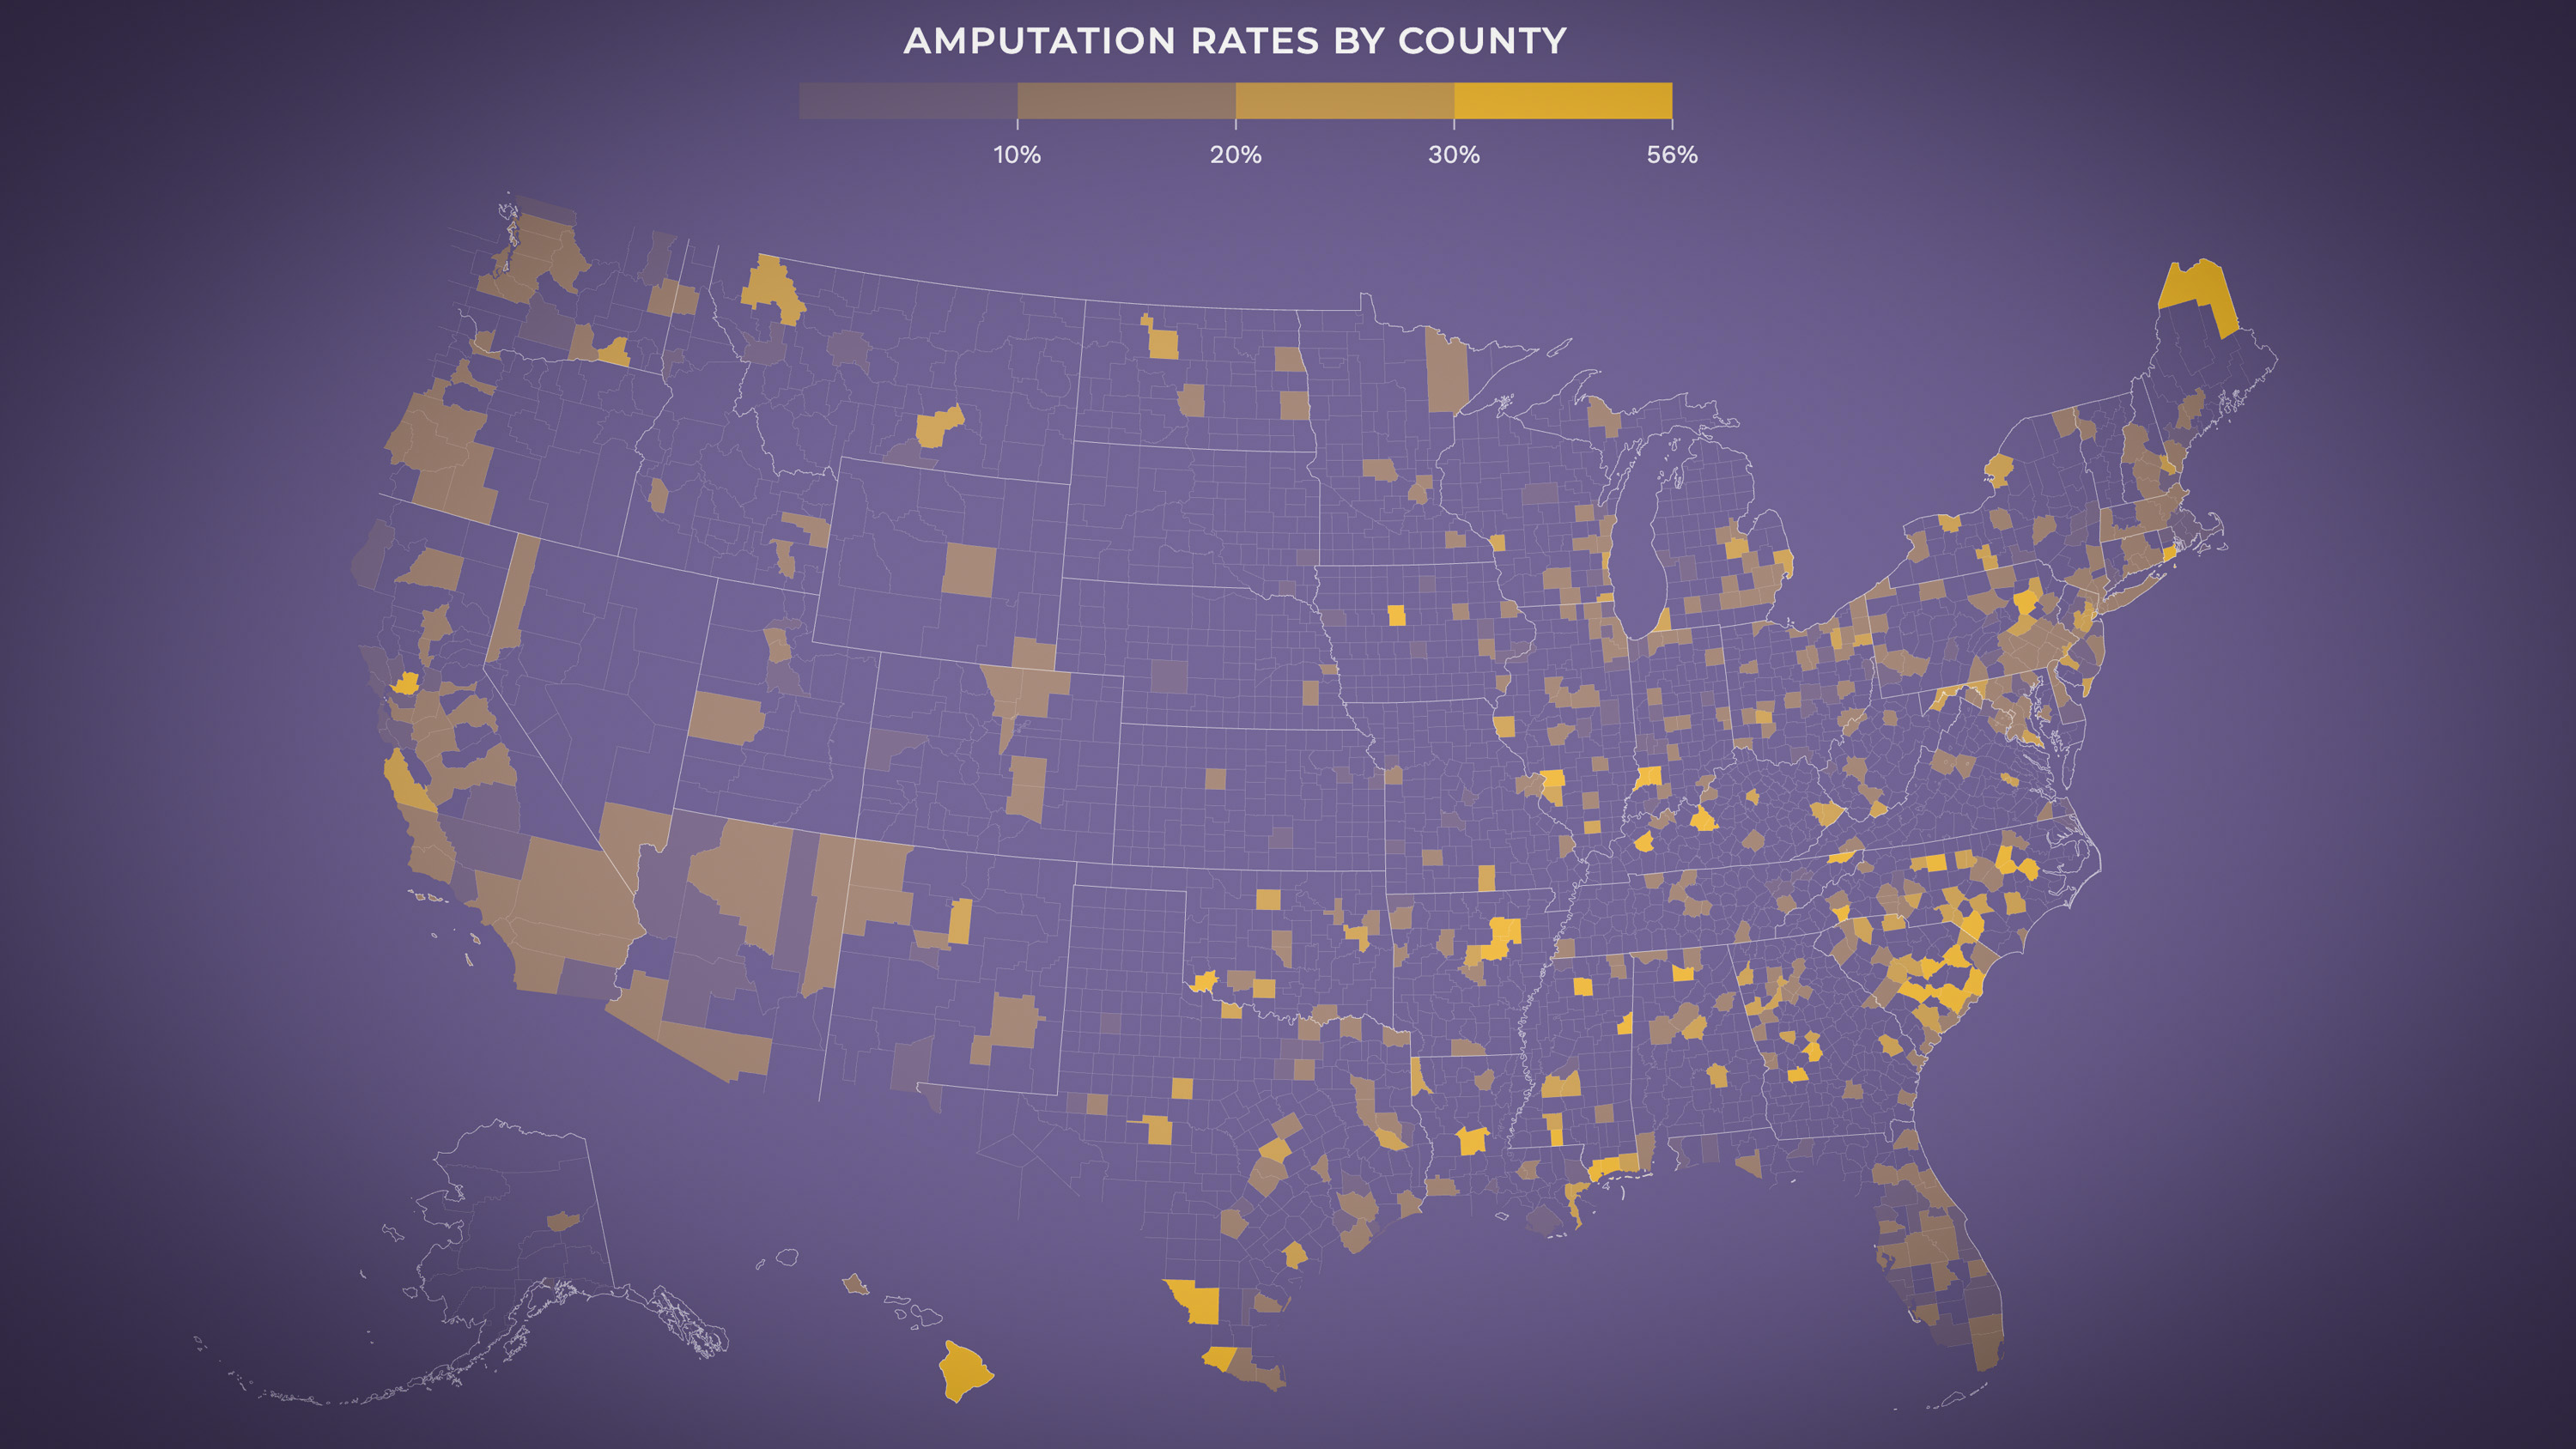
Whether those tools get used depends on who you are and where you live. Using a decade of Medicare claims — Rutherford severity codes tracked to the year before each amputation — Chude mapped how often the limb actually came off at each stage of disease. Through the early stages the amputation rate stayed in the single digits. Then, at the most advanced stage — gangrene — it leapt: nearly two in five patients lost the limb, and among Black patients, more than half. The system does little, and then it amputates.
She also asked a simpler question of the record: before the limb came off, did anyone try to save it? She looked for the procedure codes of limb salvage — the bypasses, the attempts — that should come first. She expected the gap to close at the top. At the most advanced stage, where the limb is most threatened, amputation rates across groups should converge. They didn't. Even there, Black patients were less likely to have had a salvage attempt on the record before a major amputation. "There's still so much more that was done for them," she said of other groups, "even at that very high stage, to save their limb."
The pattern is regional too. In some parts of the country, surgeons reach for salvage; in others, they reach for the saw. Same disease, different door, depending on the map.
Losing the limb is not the end of the story. It is the start of a harder one. The factors that led a patient to amputation — the advanced disease, the missed care, the neighborhood, the kind of work they do — do not disappear when the limb does. What is added is a new weight Chude calls "a compounded care-coordination burden." Before, a patient checked in with a primary-care doctor and a cardiologist. After, there is a vascular surgeon, a prosthetics team, rehabilitation, and a running fight with insurers over the wheelchairs and crutches — durable medical equipment — that are barely covered, if at all.
The burden falls on providers as well. Many want to help, Chude found, but their amputee patients now miss appointments — they lived on a fourth or fifth floor, they can no longer drive — and the clinician's day fills with social-work referrals, disability paperwork, and a system that answers every form with a demand for another. And the stakes are not small: after a major amputation, five-year mortality is high, driven in part by a body that now moves far less while the underlying disease keeps its course.
The cost does not end when the limb does, either. Chude puts a number on it:
Patients who undergo amputation accumulate more than $500,000 in Medicare spending within three years — and the gap with comparable patients who keep their limb never closes.
The prosthetics system, meanwhile, assumes a body that doesn't change. A patient is measured and fitted; then grief and depression do their work — weight lost, weight gained — and the socket no longer fits. Wearing it brings skin abrasions and pain. The rules, including a replacement window that can stretch years, leave little room to fix it. "It's a whole mess."
The changes she points to are plainer than policy language usually allows: screening for peripheral disease at routine checkups, the way blood pressure gets checked; better prosthetic coverage; and a referral made at the bedside — an appointment placed in a patient's hands before discharge — "so they are not left with figuring it out themselves."
This is a human process, and we need a much more flexible human solution to it.
Chude's research is supported by MIFF, and she was recently also recognized as a 2025 Escarce-Kington Scholar, working with mentors at Wharton and the Perelman School of Medicine. She is an Associate Fellow at the Leonard Davis Institute of Health Care Management and Economics.
